Metformin: Uses, Side Effects and Safety
Metformin: Benefits, Risks and Side Effects


Metformin is a widely prescribed medication for type 2 diabetes. It helps lower glucose primarily by reducing excess glucose production in the liver and improving the body’s response to insulin. For many adults, it is a familiar and affordable treatment, but safe use depends on kidney function, other medical conditions, side effects and individual treatment goals.
Thank you for reading this post, don't forget to subscribe!This guide explains metformin uses, metformin side effects, metformin safety, vitamin B12 concerns, extended-release forms and how clinicians assess kidney function. It prioritizes the United States and includes UK, Australian and Canadian context. It is educational, not a substitute for personal prescribing instructions.
Metformin: Uses, Side Effects and Safety—Quick Answer
Many people tolerate the drug well after an adjustment period. Severe or persistent symptoms need clinical review, and an extended-release formulation may be useful for some patients. Metformin usually does not cause low blood glucose on its own, but hypoglycemia can occur when combined with certain other diabetes treatments.
How Does Metformin Work in the Body?
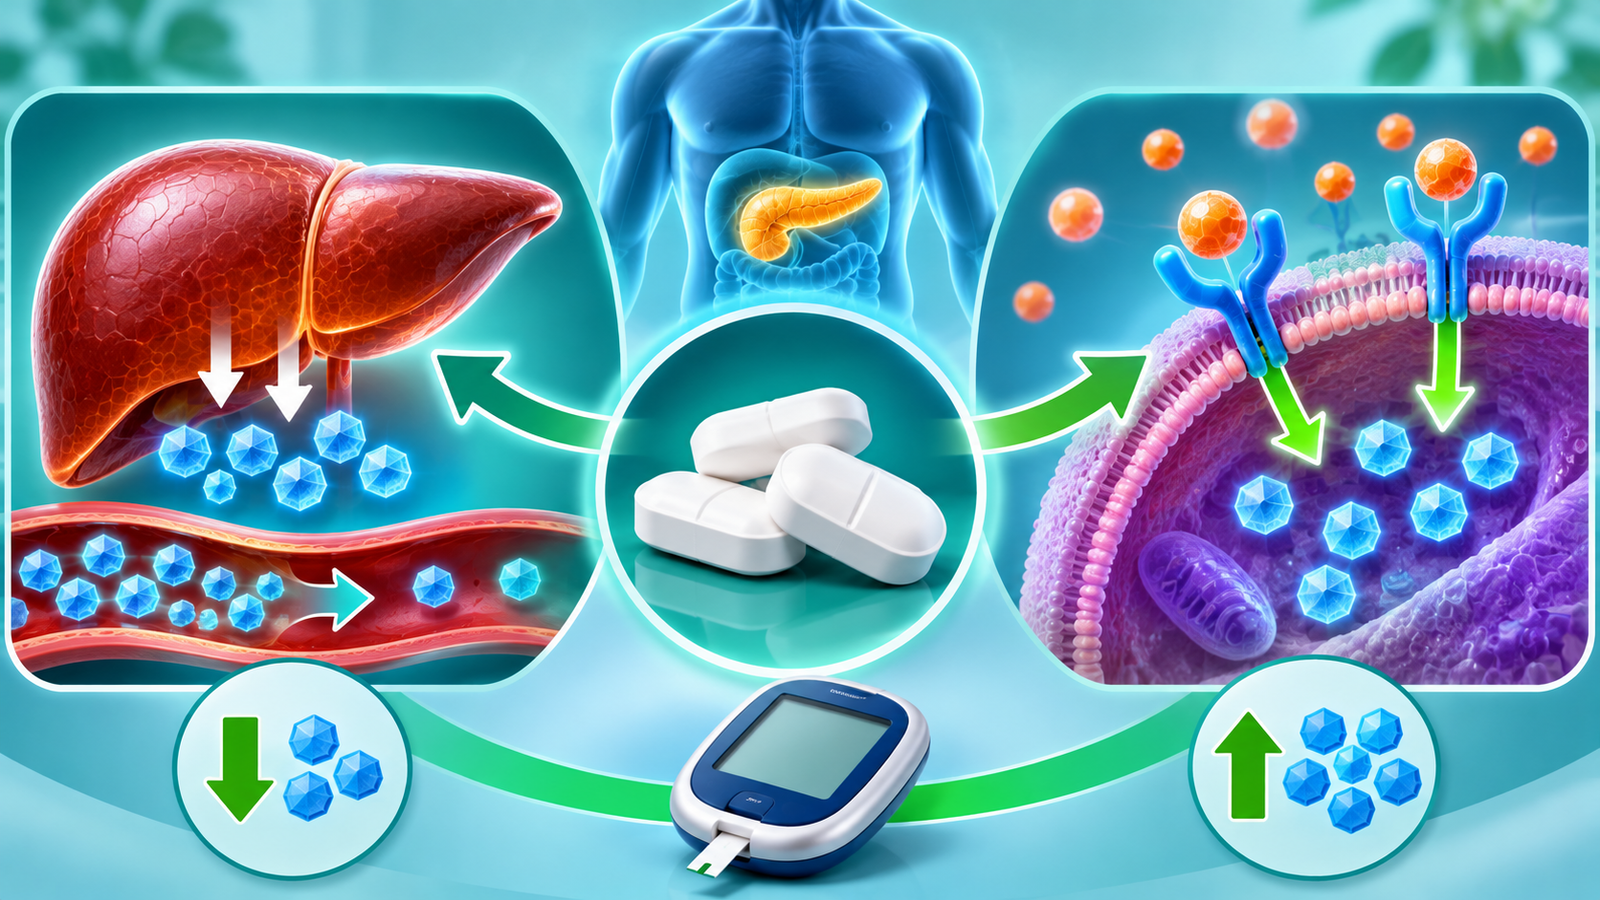
Metformin belongs to the biguanide medicine class. It primarily reduces glucose output from the liver, especially between meals and overnight, and can improve insulin sensitivity. Its effects are distinct from insulin injections, which replace or supplement insulin, and from medicines that directly stimulate the pancreas to release more insulin.
It does not remove diabetes permanently or work as an emergency treatment for diabetic ketoacidosis. Most treatment plans combine medication with nutrition support, appropriate movement and monitoring. People may still need additional medicines over time if glucose remains above their personalized goals.
Why does the liver matter for fasting glucose?
The liver normally releases glucose to help supply energy between meals. In type 2 diabetes this output may be excessive. Limiting that release can lower fasting and overall glucose, which contributes to improvement in HbA1c. The degree of improvement varies by baseline glucose, adherence and other health factors.
Related BBH reading: Diabetes Medicines: Types and Uses.
Metformin Uses in Type 2 Diabetes
The principal approved indication in the United States is to improve blood glucose control in type 2 diabetes as an adjunct to diet and exercise. It may be used alone or in combination with other medications, including insulin, when appropriate.
For someone who requires glucose lowering but has no overriding treatment consideration, the 2026 ADA Standards continue to describe metformin as a commonly used and generally affordable medicine. However, clinicians may prioritize certain GLP-1 receptor agonists or SGLT2 inhibitors in eligible people with heart disease, heart failure, chronic kidney disease or other relevant concerns.
Is metformin always the first medicine?
No. Current care is individualized. Kidney function, glucose levels, cardiovascular history, weight-related goals, adverse effects, affordability and patient preferences all influence the choice. Prescribing another medicine early does not mean metformin is ineffective.
Understanding metformin uses involves recognizing what it can do well—lower glucose with relatively little intrinsic hypoglycemia risk—and what other therapies may accomplish for specific organ-protection goals.
Metformin for Prediabetes and PCOS: Important Differences
Metformin is sometimes considered for selected adults at high risk of progressing from prediabetes to type 2 diabetes. The ADA notes that preventive medication is most relevant to particular higher-risk groups, while structured lifestyle interventions remain a cornerstone. A borderline test does not automatically justify metformin.
Clinicians may also use metformin in people with polycystic ovary syndrome (PCOS) for selected metabolic features, depending on local guidance and circumstances. This is distinct from its usual approved type 2 diabetes indication in the US. A person should understand whether the use is on-label or off-label in their location.
The medicine is not an approved weight-loss treatment simply because some people experience modest weight changes. It should not be prescribed or borrowed solely for weight management without appropriate medical assessment.
Understanding metformin uses also means distinguishing the familiar immediate-release tablet from modified-release formulations that may be easier for some patients to tolerate.
Immediate-Release vs Extended-Release Metformin
| Form | Typical administration characteristic | Practical consideration |
|---|---|---|
| Immediate release (IR) | Usually taken in divided doses according to prescription | Digestive symptoms can occur especially during initiation |
| Extended release (ER, XR, SR or modified release) | Designed to release medicine more gradually, often on a different schedule | May improve gastrointestinal tolerance for some patients; product instructions vary |
| Combination tablets | Metformin paired with another diabetes medication | Each ingredient has distinct warnings and missed-dose instructions |
A formulation switch should be made by the prescriber or pharmacist. Not all extended-release products have identical instructions. Some must be swallowed whole and should not be split, crushed or chewed. Read the label for the specific formulation.
What if the tablet looks unusual in the stool?
With some modified-release products, a harmless empty tablet shell may appear after the medicine has been released. If the product information describes this, it does not automatically mean the medication failed. Ask a pharmacist if uncertain.
How to Take Metformin Safely
Many metformin formulations are taken with food to reduce nausea or stomach upset. The precise time, number of doses and any titration plan depend on the prescription. A gradual increase may improve tolerance, but only the treating team should decide dose changes.
If a dose is missed, follow the specific label or pharmacist’s instructions. Do not double a dose to make up for a missed tablet. People taking combination products must check the instructions for all active ingredients.
Should you stop it when glucose looks normal?
No. An improved fasting reading or HbA1c may demonstrate that treatment is working. A clinician should evaluate whether to continue, adjust or replace therapy based on broader medical goals. Unexpectedly low readings should be assessed, particularly if other glucose-lowering medicines are used.
Practical metformin safety includes keeping an accurate medication list, using a single clear schedule and explaining planned surgery or contrast imaging to the team.
Related BBH reading: Type 2 Diabetes Treatment: Main Options.
Metformin Benefits and Treatment Limits
Metformin can lower HbA1c and fasting glucose and is often inexpensive. Unlike sulfonylureas or insulin, it does not usually cause hypoglycemia when used alone. It is commonly weight neutral or associated with modest weight reduction, but individual outcomes differ.
It is not the best or only treatment for every person with type 2 diabetes. Certain newer medicines have demonstrated specific cardiovascular or kidney benefits in selected patient populations. The ADA 2026 approach weighs these conditions separately from the immediate need for glucose lowering.
Importantly, long-term benefit depends on taking a suitable medicine consistently and safely. A treatment that causes intolerable side effects or cannot be afforded may need a different formulation or an alternative under clinician guidance.
Metformin Side Effects: Common and Serious
| Issue | What a person may notice | Recommended action |
|---|---|---|
| Digestive symptoms | Nausea, diarrhea, abdominal discomfort, bloating | Discuss meal timing, gradual titration or ER formulation with clinician |
| Metallic or changed taste | Unusual taste, often during early use | Tell clinician if persistent |
| Vitamin B12 deficiency | Fatigue, anemia, numbness, tingling or cognitive symptoms | Ask about testing and evaluation |
| Lactic acidosis (rare) | Severe weakness, unusual breathing, marked drowsiness or abdominal symptoms | Seek emergency assessment immediately |
Digestive effects account for many early complaints. They are frequently temporary but should not be dismissed when severe, prolonged or associated with dehydration. Recurrent vomiting, inability to drink and severe abdominal pain need clinical evaluation rather than repeated self-treatment.
Many articles about metformin side effects omit how symptoms may overlap with other conditions. Fatigue and tingling can reflect diabetes-related complications, low B12 or unrelated illnesses. A healthcare professional should assess persistent symptoms rather than assigning a single cause from a symptom list.
Managing Metformin Diarrhea, Nausea and Bloating
A helpful first step is to record when symptoms occur, the formulation, recent medicine changes and whether symptoms are associated with food. Taking the medication at a prescribed mealtime can help some people. The prescriber may recommend a slower titration or a modified-release version.
Maintain adequate fluids during mild digestive upset, unless a doctor has given restrictions. Significant vomiting or diarrhea can lead to dehydration, making medication safety more complicated. Contact the care team when unable to eat or drink normally, or when symptoms are severe.
An over-the-counter antidiarrheal medicine or supplement is not necessarily the correct answer. Persistent symptoms warrant a medication review and examination for another cause. Never increase or reduce metformin solely based on a blog recommendation.
Metformin and Vitamin B12 Deficiency
Long-term metformin use is associated with lower vitamin B12 levels in some people. Vitamin B12 is important for normal blood cell production and nerve function. Deficiency can contribute to fatigue, anemia, numbness and tingling, potentially overlapping with diabetic neuropathy.
The 2026 ADA guidance recommends periodic vitamin B12 assessment in people taking metformin, especially with anemia or peripheral neuropathy. Its guidance for older adults highlights annual monitoring for long-term users (more than four years). A person’s test schedule should be tailored to risk and medical history.
Who should discuss B12 testing?
A clinician may give extra attention to people with persistent numbness, unexplained anemia, restrictive dietary patterns, gastrointestinal absorption disorders or prolonged use. A normal blood glucose reading does not rule out a nutritional deficiency.
Can a supplement correct the problem?
If deficiency is confirmed, a clinician can recommend appropriate oral or injectable replacement based on the cause, severity and symptoms. Self-prescribing injections without evaluation is unnecessary and may delay diagnosis of another condition.

Metformin and Kidney Function: eGFR Explained
Metformin is cleared through the kidneys. Reduced kidney function may increase accumulation and the risk of serious adverse effects. Doctors generally use estimated glomerular filtration rate (eGFR), not only serum creatinine, when assessing whether metformin is appropriate.
| eGFR (mL/min/1.73 m²) | US prescribing-information position | Clinical implication |
|---|---|---|
| 60 or above | Generally suitable if no other contraindication | Continue routine kidney reassessment |
| 45–59 | Often usable, but assess individual risks and monitoring | Additional caution during acute illness or other risk factors |
| 30–44 | Starting metformin is not recommended in US labeling | If already taking it, clinician assesses benefit versus risk and potential changes |
| Below 30 | Contraindicated in US labeling | Do not use; specialist-directed alternative needed |
These eGFR ranges summarize US prescribing information; exact brand guidance and national rules may differ. Some experts consider lower doses for selected established users with eGFR 30–44, but patients should never interpret the chart as a personal dosing instruction.
Kidney function can worsen temporarily with severe dehydration, infection or other acute illness. For this reason, metformin safety involves monitoring kidney status over time, discussing significant illness and following individualized sick-day instructions.
Metformin-Associated Lactic Acidosis: Rare but Serious
Lactic acidosis occurs when the body develops a dangerous acid-base disturbance involving lactate. Metformin-associated lactic acidosis is rare, but can be life-threatening. Risk is higher in circumstances such as substantial kidney impairment, hypoxia, severe illness, significant dehydration or other contraindications described in product labeling.
Warning signs can include unusual severe tiredness, pronounced weakness, muscle pain, abdominal discomfort, vomiting, sleepiness and difficult or rapid breathing. These signs are not specific, but require emergency evaluation when serious or concerning. Do not wait for a home glucose meter to become dramatically abnormal.
Metformin, Contrast Scans and Surgery
Some iodinated contrast imaging procedures require a temporary metformin interruption. US labeling advises holding it at or before certain contrast procedures in people with eGFR 30–60, particular heart or liver-related risks, or when intra-arterial contrast is used. Kidney function may need reassessment before restarting.
Not every imaging study requires the same action. The choice depends on the planned procedure, kidney function, hydration and local protocol. Always tell the radiology department and prescribing clinician that you take metformin and follow their direct instructions.
What about major operations or illness?
Fasting, anesthesia, dehydration and reduced oxygen delivery can alter medicine safety. The clinical team should provide a medication-specific plan. Do not independently stop every diabetes treatment, particularly when insulin is prescribed.
Related BBH reading: Low Blood Sugar: Symptoms and Treatment.
Does Metformin Cause Low Blood Sugar?
When used alone, metformin has a low risk of hypoglycemia because it does not generally force the pancreas to release insulin. Low glucose can become more likely when combined with insulin or medications such as sulfonylureas, or under other clinical circumstances.
Symptoms of hypoglycemia include sweating, shaking, hunger, palpitations and confusion. Follow the personalized low-glucose treatment plan provided by the diabetes team. Severe confusion, seizures or inability to swallow requires emergency help.
The medication’s generally low intrinsic risk does not mean a person should ignore recurrent low readings or symptoms. Review the full medicine list, food intake, activity and measurement technique with a clinician.
Metformin, Alcohol and Medicine Interactions
Excessive alcohol use can increase the risk of lactic acidosis and may affect glucose management. Some other drugs alter kidney function or metformin transport and may affect its safety or concentration. A pharmacist should review prescription medications, supplements and recent changes.
Tell clinicians about conditions that increase dehydration risk, medicines that affect kidney function and any upcoming procedures. Ask before starting products marketed for “blood sugar detox” or “natural diabetes reversal,” since their quality and interactions may be uncertain.
A careful interaction review is part of metformin safety. This is especially important when several clinicians prescribe medicines for diabetes, blood pressure, chronic pain or heart disease.
Metformin in Pregnancy, Older Age and Other Conditions
Pregnancy and pregnancy planning
Pregnancy requires specialized glucose targets and medication decisions. Metformin crosses the placenta and is used in some clinical situations, but recommendations and the balance of benefits and uncertainties vary. Do not start, stop or switch treatment during pregnancy without obstetric and diabetes specialists.
Older adults
Age itself is not an automatic reason to stop metformin. However, frailty, changing kidney function, dehydration risk and long-term vitamin B12 deficiency may make closer monitoring important.
Liver disease and serious illness
Significant hepatic impairment, acute metabolic acidosis, severe infection and disorders involving poor oxygen delivery call for a specific medical review. A history of these conditions may influence whether metformin is appropriate.
A person with type 1 diabetes requires insulin therapy. Metformin must never replace prescribed insulin when clinically essential.
Related BBH reading: Diabetes Diagnosis: Which Tests Are Used?.
Which Tests and Follow-Up Checks Matter?
| Check | Why clinicians consider it |
|---|---|
| HbA1c and glucose trends | Assess effectiveness alongside personalized goals |
| eGFR and renal function | Guide safe continuation, interruption or alternative therapy |
| Vitamin B12 when appropriate | Assess anemia, neuropathy or long-term depletion risk |
| Side effects and medicine list | Address adherence, interactions and formulation tolerance |
| Blood pressure, lipids and other risk assessment | Provide comprehensive diabetes care beyond glucose |
Monitoring frequency depends on health status, the stability of kidney function and other medications. Diabetes care should also review eye, kidney and foot health as appropriate. Patients can bring a written symptom log and any available blood glucose records to appointments.
In a typical consultation, assessing metformin uses alongside heart and kidney health helps determine whether treatment needs to be expanded, changed or simplified. Do not chase a lower A1C if the result requires unsafe hypoglycemia or intolerable side effects.
Across countries, metformin uses and licensed indications should be checked against local prescribing information because the medicine may be used in different clinical contexts.

Metformin Guidance in the USA, UK, Australia and Canada
| Country | Guidance and access context | Practical takeaway |
|---|---|---|
| USA — primary | FDA-approved product labels and ADA Standards 2026 | eGFR-based precautions, B12 consideration, medication selection tailored to comorbidity |
| United Kingdom | NHS patient advice and NICE type 2 diabetes guidance | Immediate and modified-release metformin options, NHS medicine support and individualized risk review |
| Australia | Australian medicine product information and diabetes professional resources | Local brands and prescribing information; kidney and illness-related precautions |
| Canada | Diabetes Canada pharmacologic guidelines and local product labels | Cost, kidney function and complementary heart-kidney therapies influence care |
The underlying pharmacology is the same across countries, but local labeling, brand availability, prescription requirements and reimbursement can differ. People should consult their own pharmacist or clinician instead of applying a dosing schedule or imaging rule copied from another country’s website.
For US readers, current FDA labeling and ADA 2026 Standards are the primary references for this article. NHS, Australian and Canadian resources provide context rather than permission to self-prescribe.
Related BBH reading: Can Type 2 Diabetes Go Into Remission?.
Common Myths About Metformin
Myth: Metformin damages every person’s kidneys
Metformin is primarily cleared through the kidneys; impaired kidney function can make it unsafe. That is different from saying it directly damages everyone’s kidneys. eGFR monitoring helps clinicians assess suitability.
Myth: Normal sugar readings mean you should stop it
Improved readings may reflect medicine effectiveness. Changes require evaluation of treatment goals, other conditions and risk of glucose rising again.
Myth: It always causes vitamin B12 deficiency
Risk increases with prolonged use, but not all users become deficient. Testing and replacement should be guided by symptoms and individualized clinical assessment.
Myth: Extended-release is a stronger medicine
Extended-release changes how the medication is delivered, not whether it magically becomes stronger. Dosing equivalence and instructions depend on the specific product.
Myth: Metformin can cure type 2 diabetes
It can support glucose control, but does not establish a permanent cure. Formal remission has separate criteria and requires clinician confirmation.
Metformin Frequently Asked Questions
What is metformin mainly used for?
It is widely used to improve blood glucose control in people with type 2 diabetes, sometimes alongside other medicines.
Does metformin cause diarrhea?
Yes. Diarrhea and nausea are among its more common side effects. Meal timing, slower titration or extended-release products may help under clinician guidance.
What is the difference between regular and XR metformin?
XR or ER products release medication more gradually and may improve tolerability for some people. Follow product-specific directions.
Can metformin cause vitamin B12 deficiency?
Yes, particularly with long-term use. Discuss testing if you experience anemia, fatigue, tingling or numbness.
Is metformin safe with kidney disease?
It depends on eGFR and other risk factors. US labeling contraindicates it when eGFR is below 30 and discourages starting it at 30–45.
Can I take metformin before a CT scan?
Some contrast-enhanced scans require a temporary pause, while others do not. Ask the radiology and prescribing teams about your specific procedure.
Does it cause low blood sugar by itself?
Metformin alone rarely causes hypoglycemia, but risk can rise when combined with insulin or certain other medicines.
Should I take it without food?
Many formulations are taken with food to improve tolerance. Follow your own prescription and pharmacist’s instructions.
Related BBH Articles and Support
Scientific Sources and Medical Disclaimer
- American Diabetes Association: Standards of Care in Diabetes—2026, Pharmacologic Approaches
- ADA Standards 2026: Older Adults and Metformin Monitoring
- US DailyMed: Metformin Hydrochloride Prescribing Information
- NHS: Metformin Uses and Side Effects
- NICE: Type 2 Diabetes in Adults
- Australian Commission: Metformin Medicine Information
- Diabetes Canada: Clinical Practice Guidelines



