Frequent Urination and Diabetes: Causes & Signs
Why Diabetes Causes Frequent Urination

BBH Physical Health · Diabetes & Blood Sugar · Evidence-based health education
Thank you for reading this post, don't forget to subscribe!You may notice a change at work before you notice it at home: another bathroom visit during a meeting, a night interrupted by repeated toilet trips, or a growing need to carry a water bottle. It is natural to wonder whether blood sugar is responsible. However, urinary frequency has several possible causes, and the pattern of urination is often more informative than the number of visits alone.
Frequent urination and diabetes are connected because sufficiently elevated blood glucose can increase urine production. Yet needing to urinate often does not automatically mean that the kidneys are making too much urine. A person with a urinary tract infection, an overactive bladder or a prostate problem may visit the toilet repeatedly while passing very little.
This guide explains why the patterns differ, which accompanying symptoms deserve attention, when laboratory testing is useful and how clinicians investigate urinary changes. The goal is to help readers recognize meaningful changes without diagnosing themselves from an internet checklist.
1. Why Does Diabetes Cause Frequent Urination?
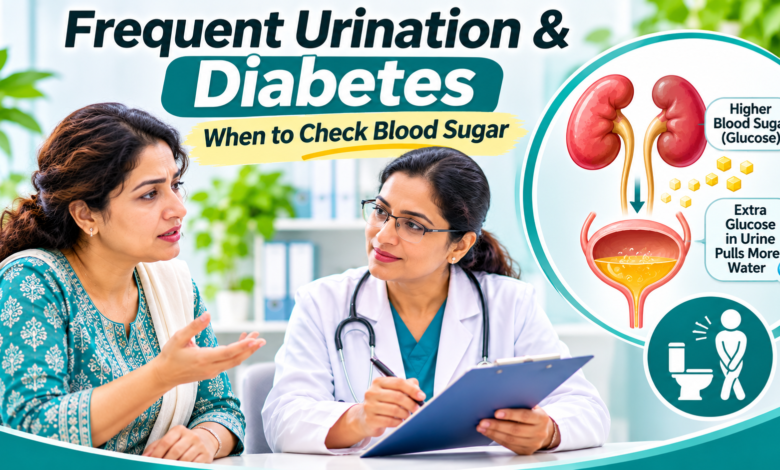
Glucose circulates in the blood and is normally filtered and reclaimed by the kidneys. When blood glucose becomes sufficiently high, the amount filtered can exceed the kidneys’ capacity to reabsorb it. Glucose then appears in the urine. Because glucose is osmotically active, it draws additional water into the urine. Clinicians call this process osmotic diuresis.
The result can be a noticeably greater volume of urine, with trips to the bathroom occurring during the day and overnight. Fluid loss can also increase thirst, so frequent urination and intense thirst often occur together. The specific glucose level at which glucose appears in the urine varies between individuals, and this mechanism cannot be used as a home diagnostic test.
This explains why someone might drink more yet continue losing fluid. The thirst is partly a response to the water being lost. If the underlying glucose problem is not addressed, drinking alone does not correct it, although maintaining appropriate hydration matters while medical advice is sought.
Does this happen in both type 1 and type 2 diabetes?
It can. Type 1 diabetes may produce symptoms over a relatively short period, particularly when the body becomes severely insulin deficient. Type 2 diabetes often evolves more gradually, and some people do not recognize classic symptoms. The duration and intensity of urination do not establish diabetes type. If severe thirst and rapidly worsening illness occur with weight loss, urgent evaluation is important.
2. Frequent Urination vs Polyuria: A Critical Difference
When evaluating frequent urination and diabetes, here is the distinction many short symptom articles overlook. Urinary frequency describes going to the bathroom often. Polyuria describes producing an unusually large total volume of urine. Both can lead to many toilet visits, but they do not mean the same thing.
| Question | More suggestive of excess urine production | More suggestive of bladder urgency or irritation |
|---|---|---|
| Amount each visit | Often substantial | May be small |
| Associated feeling | Thirst, larger daily fluid losses | Urgency, burning, pressure or leakage |
| Possible causes | Hyperglycemia, diuretics, high fluid intake, other disorders | UTI, overactive bladder, prostate or pelvic conditions |
Some clinical references use a daily adult urine volume above approximately three liters to describe polyuria, although exact definitions and interpretation depend on body size and context. Readers should not attempt to estimate an entire day’s urine volume from memory; clinicians may use a measured frequency-volume diary if necessary.
An example makes the distinction easier. One individual passes a large amount of pale urine every few hours and drinks more than usual. Another feels the urge every thirty minutes but passes a few drops with burning. Their symptoms both involve repeated bathroom visits, yet the second pattern deserves assessment for infection or bladder irritation rather than automatically being attributed to diabetes.
3. Which Other Diabetes Symptoms May Appear With Frequent Urination?
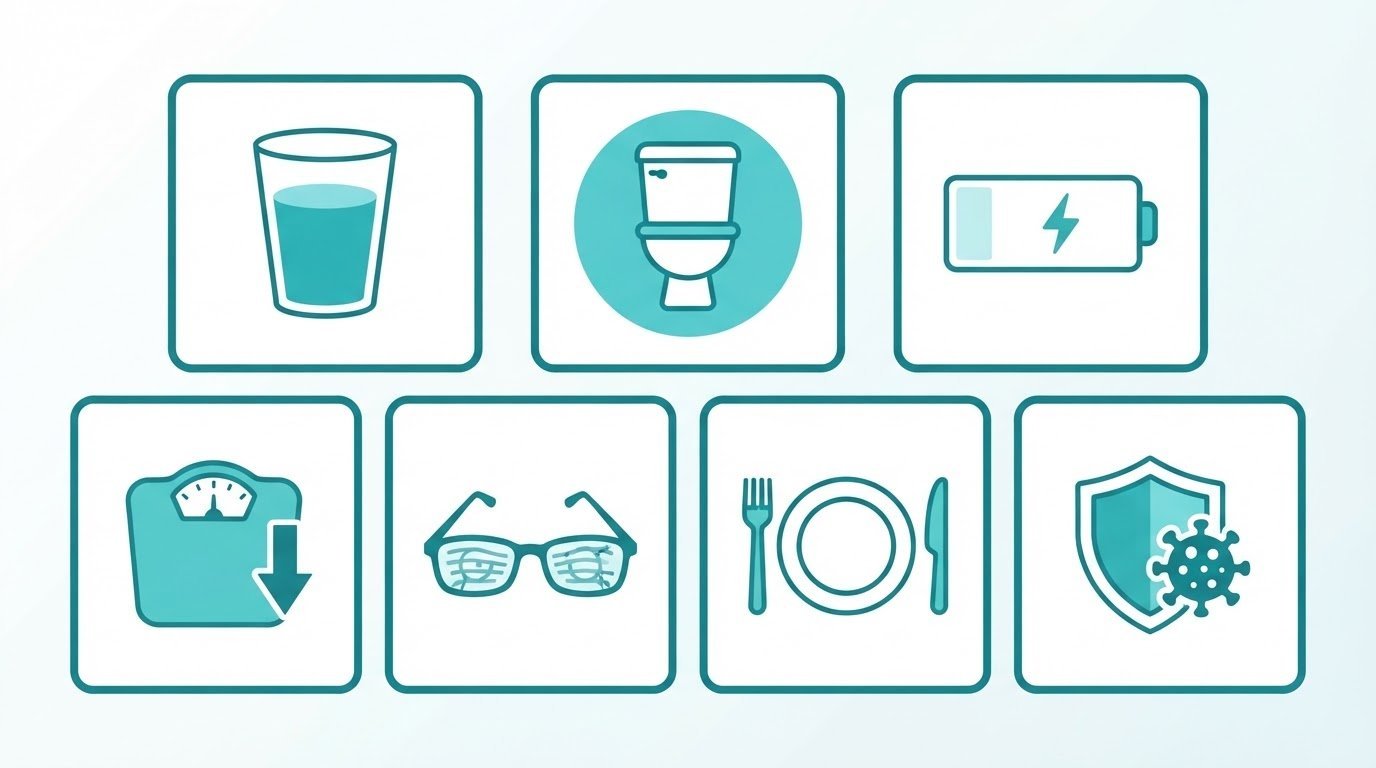
High urine output is more suggestive of a glucose-related cause when it appears alongside other classic hyperglycemia symptoms. Increased thirst is particularly relevant because of the fluid loss described above. Unexplained weight loss, fatigue, blurred vision and recurrent infections may also warrant investigation. None of these findings is unique to diabetes.
- Unusual thirst: needing considerably more water than before, sometimes at night.
- Unexpected weight loss: a change not explained by deliberate diet or activity modifications.
- Fatigue: reduced energy that persists after ordinary rest, although sleep disruption itself may contribute.
- Blurred vision: shifting focus or clarity, which can have numerous causes.
- Genital or urinary infections: recurring infection symptoms that require examination and appropriate treatment.
An absence of other warning signs cannot rule out diabetes. Some people discover high glucose at a routine health check while feeling entirely well. Explore Can You Have Diabetes Without Symptoms? for a more detailed explanation.
Is urination alone enough to diagnose diabetes?
No. A urinary symptom cannot establish the cause by itself. Even glucose detected on a urine dipstick does not replace the laboratory blood tests required to diagnose diabetes. A clinician may use urine findings to guide further testing, particularly if infection or kidney concerns are also present.
4. Frequent Urination at Night and Diabetes: What Is Nocturia?
Nocturia means waking from sleep to urinate. It can affect sleep quality and daytime functioning, but waking at night is not synonymous with diabetes. A person who produces excessive urine around the clock may need to pass urine overnight. Another may have relatively normal overall urine volume but a bladder that cannot store enough comfortably during sleep.
Other contributors include drinking a large amount close to bedtime, alcohol, caffeine, medicines that increase urine output, sleep apnea, lower-leg fluid that returns to circulation during sleep and age-related bladder changes. A clinician may investigate several causes at once rather than assuming there is one explanation.
Why number of night-time trips does not settle the question
One visit may be bothersome to some people while several may be familiar to others; the significance depends on age, amount passed, sleep pattern and associated symptoms. There is no single overnight bathroom count that can diagnose diabetes. The key question is whether the pattern is new, persistent, worsening or accompanied by other concerning changes.
Someone who wakes because they are already awake for another reason and then chooses to urinate may be experiencing a different pattern from someone awakened by a full bladder. Noting this distinction can help during an assessment.
5. Other Causes of Frequent Urination Besides Diabetes
It is important to avoid reducing every urinary complaint to blood sugar. Several common and uncommon conditions can cause frequency or increased urine production, and some require prompt treatment.
Urinary tract infection
A UTI may cause burning, urgency, lower abdominal discomfort or frequent small-volume urination. Fever, flank pain or worsening illness may indicate infection involving the kidneys. A urine test and clinical review can help identify the cause. Treatment depends on the findings, not on the assumption that every urinary symptom is diabetic.
Overactive bladder and pelvic-floor conditions
An overactive bladder can create a sudden compelling need to urinate, sometimes accompanied by leakage. Pelvic-floor conditions may also affect control. The total amount of urine may remain normal even when bathroom trips are frequent. Assessment may include a bladder diary, examination and evaluation for alternative conditions.
Prostate enlargement or incomplete emptying
In men, difficulty starting urine, a weak stream, dribbling and a sensation of incomplete emptying may point toward urinary obstruction or prostate-related disease. This pattern differs from passing large quantities of urine because of hyperglycemia. Both problems can occasionally coexist.
Medicines, drinks and other disorders
Diuretic medicines increase urine production intentionally. Caffeine and alcohol may aggravate urinary symptoms in some people. Certain diabetes treatments, including SGLT2 inhibitors, increase urinary glucose excretion and may alter urination. Pregnancy, kidney conditions, diabetes insipidus and substantial habitual fluid intake are other possibilities. Diabetes insipidus is a different disorder involving water regulation and is not caused by the high blood sugar of diabetes mellitus.
The most appropriate evaluation depends on the whole picture: urination volume, thirst, pain, medications, fluid intake, pregnancy status and medical history.
6. How Do Doctors Test Frequent Urination and Possible Diabetes?
For frequent urination and diabetes, medical evaluation often starts with questions rather than an immediate diagnosis. A clinician may ask when the change began, how much urine is passed, whether there is pain, what medicines are taken and how much fluid is consumed. Examination may be appropriate, and urine analysis can help identify infection, blood or glucose.
When blood sugar is a concern, laboratory testing follows established diagnostic criteria. Common options include HbA1c, fasting plasma glucose and a 75-g oral glucose tolerance test. A home finger-stick meter can provide useful information for someone already monitoring diabetes, but it is not normally used alone to diagnose the condition.

Blood glucose thresholds for nonpregnant adults
| Test | Prediabetes | Diabetes |
|---|---|---|
| HbA1c | 5.7–6.4% | 6.5% or higher |
| Fasting plasma glucose | 100–125 mg/dL | 126 mg/dL or higher |
| Two-hour 75-g OGTT | 140–199 mg/dL | 200 mg/dL or higher |
With classic symptoms of hyperglycemia or a hyperglycemic crisis, a random laboratory plasma glucose value of at least 200 mg/dL may meet diagnostic criteria. Otherwise, confirmation with additional abnormal testing is generally required. Certain health conditions can make HbA1c misleading, so the clinician selects and interprets tests accordingly.
Pregnancy has different screening and diagnostic rules. For explanations of test preparation and confirmation, continue to Diabetes Diagnosis: Which Tests Are Used?.
7. Does Frequent Urination Mean Blood Sugar Is Very High?
Not necessarily. There is no reliable equation linking the number of bathroom trips to a particular glucose concentration. Urine output depends on fluid intake, the kidneys’ handling of glucose, medicines and other health conditions. Two people with the same laboratory glucose result may not have identical symptoms.
It is also possible to have high glucose with few obvious symptoms. The reverse is true as well: someone with frequent urination may have normal glucose levels because the cause lies elsewhere. This is why symptom intensity alone cannot substitute for appropriate testing.
If you already have diabetes and notice a new pattern, review any monitoring plan provided by your care team and discuss whether the change could reflect glucose control, medication effects, a UTI or a separate bladder problem. Do not stop or adjust a prescribed medicine based solely on this article.
8. What About Diabetes and Long-Term Bladder Problems?
The relationship between frequent urination and diabetes can involve more than excess glucose in urine. Not every urinary problem in someone with diabetes is the direct result of excess glucose in urine. Over time, diabetes can affect autonomic nerves involved in bladder function. Some people experience urgency, leakage or difficulty emptying the bladder completely. Urinary infections can complicate the picture.
A person with impaired bladder emptying may feel frequent urges despite retaining urine. Someone else may have reduced awareness of bladder fullness. These patterns require clinical evaluation because management differs from treatment of glucose-related polyuria. Persistent incontinence, recurrent infections or a weak stream should be discussed with a professional.

NIDDK provides patient guidance on diabetes-related sexual and bladder problems, including the need to evaluate urinary symptoms rather than assuming they all result from high glucose. Improving glucose management may help some symptoms, while other bladder conditions require their own treatment.
9. When Is Frequent Urination an Emergency?
Most urinary changes warrant a timely assessment, but certain combinations call for urgent or emergency care. A person who cannot urinate despite a painfully full bladder needs immediate medical help. Fever with flank pain, severe weakness or worsening illness may indicate a serious urinary or kidney problem.
- Repeated vomiting, abdominal pain, deep or rapid breathing, fruity-smelling breath or confusion, particularly with intense thirst, may indicate diabetic ketoacidosis or another metabolic emergency.
- Severe dehydration, fainting, marked drowsiness or an inability to retain fluids needs urgent assessment.
- Inability to pass urine, severe lower abdominal pain or significant blood in urine deserves prompt clinical review.
- Fever or chills with back or side pain may indicate a kidney infection and should not be ignored.
Type 1 diabetes can first appear through a medical emergency, and serious hyperglycemia may also occur in people with type 2 diabetes. Do not delay emergency care while waiting for a routine fasting test.
10. A Practical 24-Hour Urination Diary
A short diary may help explain a symptom pattern more clearly to a healthcare professional. It need not be complicated, and it should never delay care when warning signs are present. Record approximate times of drinks and bathroom visits, whether each void seems small or large, and any urgency, burning, leakage or thirst.
A clinician may request a structured frequency-volume chart with measured amounts if polyuria or nocturnal urine production needs to be distinguished from bladder frequency. Do not force extra water to complete a diary, and do not restrict fluid excessively to reduce the number of bathroom visits.
| What to record | Useful detail |
|---|---|
| When it happened | Day or night, including whether the urge woke you |
| Amount passed | Small, moderate or large; measured if asked |
| Other sensations | Burning, urgency, incomplete emptying, thirst |
| Drinks and medicines | Timing, caffeine and prescribed diuretics |
11. What Can Help While Waiting for a Medical Appointment?
The safest first response is to identify whether symptoms are mild and stable or suggest an urgent problem. If you have newly increased urine output alongside thirst, arrange a medical assessment rather than trying to compensate with extreme fluid restriction or an untested supplement.
Drink fluids according to your usual medical guidance; people with kidney or heart disease may have individualized fluid limits. Avoid suddenly stopping diuretics, insulin or other prescribed medicines. When infection is possible, seek assessment rather than repeatedly self-treating symptoms with leftover antibiotics.
If glucose is high, professional advice may include a treatment or monitoring adjustment. If the problem is a UTI, prostate disorder or overactive bladder, care may be quite different. A thoughtful assessment helps avoid treating the wrong cause.
12. Frequently Asked Questions About Frequent Urination and Diabetes
Can frequent urination be the first sign of diabetes?
Yes. Increased urine volume may be an early recognized symptom when blood glucose rises sufficiently. However, it can also have other causes, and some people with diabetes notice no symptoms.
How many times a day is too often?
There is no universal number that diagnoses a condition. Fluid intake, age, urgency, urine volume and changes from your usual pattern are important. A new persistent change merits assessment.
Does frequent urination from diabetes usually involve large amounts?
Glucose-related osmotic diuresis often increases total urine output. Repeated small-volume urination may suggest bladder irritation or a different mechanism, although patterns can overlap.
Will drinking less water stop diabetic urination?
Restricting fluid does not correct the cause of glucose-related urine loss and may worsen dehydration. Discuss symptoms and appropriate hydration with a clinician.
Can diabetes cause nighttime urination?
Yes, but nocturia also occurs with sleep disorders, evening fluids, medications and urinary tract or bladder conditions.
Does burning urination indicate diabetes?
Burning is more suggestive of irritation or infection than glucose-related polyuria alone. A urine test and clinical assessment may be appropriate.
Can frequent urination continue after glucose improves?
Yes. Some urinary symptoms arise from infection, bladder dysfunction, medicines or other causes even when glucose management improves.
Should I check glucose if I feel fine otherwise?
A new unexplained urinary pattern can justify discussing glucose testing, particularly when risk factors are present. Feeling well does not exclude diabetes.
Conclusion: Notice the Pattern, Then Check the Cause
The relationship between frequent urination and diabetes is real, but it is more specific than simply going to the toilet often. High glucose can increase total urine output, while infection, urgency syndromes and prostate conditions may lead to repeated small-volume trips. The distinction helps make medical conversations more productive.
Record the change, consider other symptoms and ask whether urine testing and laboratory glucose testing are appropriate. When urgent warning signs occur, seek immediate care. For routine concerns, an accurate diagnosis is more useful than guessing from the number of bathroom visits.
Scientific References




